The scan report usually arrives with a line that was not on anyone’s mind: “bicornuate uterus.” Sometimes it is found during a fertility workup. Often it turns up on a routine early pregnancy scan, or is mentioned for the first time after a caesarean. Either way, the word sounds rare and a little alarming, and a quick search fills the screen with lists of complications.
I’m Dr. Suganya Venkat, an OB-GYN with more than 15 years of experience, and the first thing I tell women with this finding is that most of them can conceive, and many carry a pregnancy to term without problems. What the diagnosis mainly changes is how closely the pregnancy is monitored.
This post covers what a bicornuate uterus is, how it differs from a septate uterus (the condition it is most often confused with), what the research shows about pregnancy, why surgery is seldom part of the plan, and the practical steps that help.
What a Bicornuate Uterus Is
Before birth, the uterus forms from two tubes of tissue called the Müllerian ducts. Normally they fuse along their length into one pear-shaped organ, and the wall left between them then dissolves to leave a single cavity.
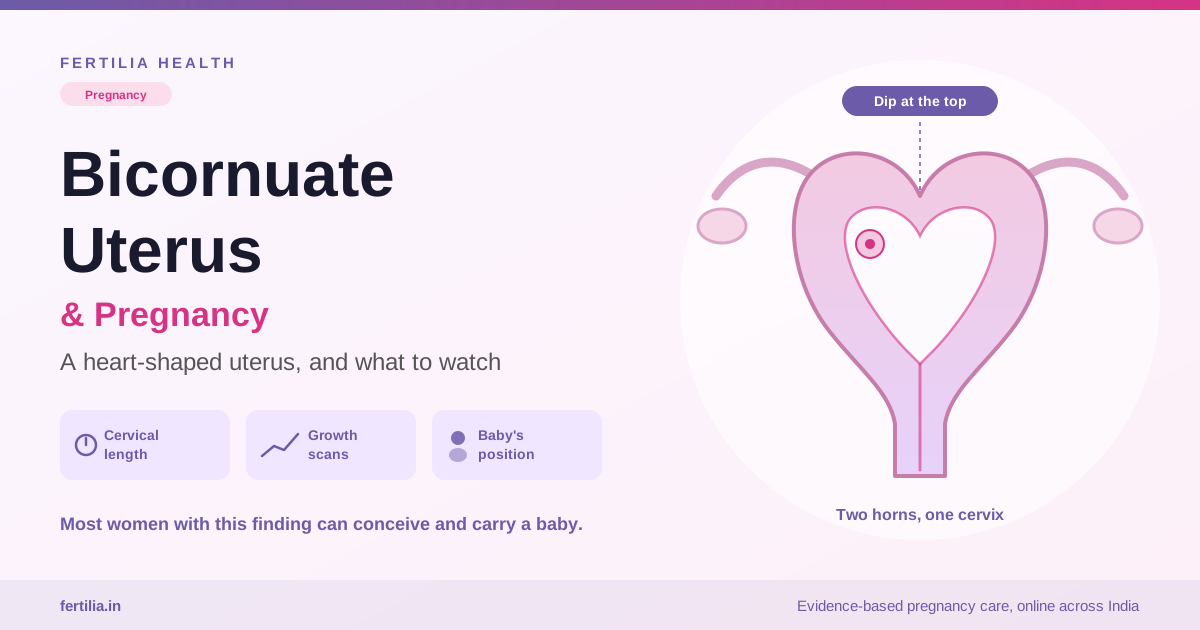
In a bicornuate uterus, the two ducts do not fuse completely at the top. The result is a uterus with two “horns” (bicornuate means two-horned) joined lower down, giving it a heart shape from the outside. There is a dip in the outer wall at the top of the uterus, and the cavity inside is divided into two connected halves.
Doctors describe it by how far the division reaches. In a partial bicornuate uterus, the split affects only the upper part. In a complete bicornuate uterus, it extends down towards the cervix. The two main classification systems in use today place it in their own way: the European ESHRE/ESGE system calls it a “bicorporeal uterus”, class U3 (Grimbizis GF et al., Hum Reprod, 2013, PMID 23771171), and the American Society for Reproductive Medicine published an updated classification of Müllerian anomalies in 2021 (Pfeifer SM et al., Fertil Steril, 2021, PMID 34756327). Your report may use either set of terms.
How common is it? Uterine shape anomalies of all types are more frequent than most people assume. A systematic review of 94 studies found them in about 5.5% of women in unselected populations when the best imaging tests were used, with the arcuate uterus (a shallow, usually harmless dip) the most common type (Chan YY et al., Hum Reprod Update, 2011, PMID 21705770). A bicornuate uterus is much less common than that overall figure. In a large population-based cohort, 0.15% of pregnant women had one (Mastrolia SA et al., J Matern Fetal Neonatal Med, 2017, PMID 27903074).
Bicornuate or Septate: Why the Difference Matters
These two are mixed up more than any other pair of uterine findings, and the mix-up changes treatment.
| Bicornuate uterus | Septate uterus | |
|---|---|---|
| What happened during development | The two ducts did not fully fuse | The ducts fused, but the wall between them did not dissolve |
| Outer shape of the uterus | Heart-shaped, with a dip at the top | Normal, single dome |
| Inside the cavity | Two connected halves | A band of tissue dividing the cavity |
| Usual surgical option | Rarely operated on; major uterine surgery if ever | Hysteroscopic resection through the cervix |
A septum is a band of tissue that can be removed through the cervix in a day procedure. A bicornuate uterus has no such band to remove; the shape of the organ itself is different. If you have been told you have a septate uterus, our post on septate uterus, pregnancy outlook and when surgery helps covers that condition in detail.
Two other anomalies are sometimes confused with a bicornuate uterus. A didelphys uterus has two completely separate uterine bodies, usually with two cervices. A unicornuate uterus develops from only one duct, so it is a single, smaller “horn”. Each has its own pattern in pregnancy.
How It Is Diagnosed
The key question is the outer shape of the uterus, and not every test can see it.
- 2D ultrasound and HSG can show that the cavity looks divided, but they cannot reliably tell a bicornuate uterus from a septate one. An HSG, in particular, outlines only the inside of the cavity. Our walkthrough on reading your HSG report explains why a “bicornuate” label on an HSG needs confirmation before any decision is made.
- 3D transvaginal ultrasound shows the cavity and the outer contour together, which is what separates the two conditions. In experienced hands it usually settles the question. If you are new to this kind of scan, our guide to the transvaginal scan and what it shows is a useful starting point.
- MRI is used when the 3D picture is unclear or the anatomy is complex.
A kidney check is often added. The uterus and the urinary tract develop next to each other in the embryo, so a difference in one sometimes comes with a difference in the other, such as a single kidney. A 2025 chart review notes that roughly 20 to 40% of girls and women born with a kidney anomaly also have a Müllerian anomaly (Rosenberg S et al., J Pediatr Surg, 2025, PMID 40451384). A simple kidney ultrasound is a reasonable addition once a uterine anomaly is confirmed.
Can You Get Pregnant With a Bicornuate Uterus?
In most cases, yes. A bicornuate uterus does not block the tubes, stop ovulation, or change egg quality. A systematic review that grouped the bicornuate, unicornuate and didelphys uteri together as “unification defects” concluded that none of them reduces fertility (Chan YY et al., Ultrasound Obstet Gynecol, 2011, PMID 21830244).
That matters for women who are trying to conceive and have just been given this diagnosis. If conception is taking longer than expected, the usual fertility workup (ovulation, tubes, semen analysis, thyroid and so on) still applies, and the uterine shape is usually not the reason. If you have had two or more losses, our guide to recurrent miscarriage tests explains what a full workup covers, so that the uterus is not blamed before other causes are checked.
If you have just been told you have a bicornuate uterus and want to understand what it means for your plans, you can talk it through with Dr. Suganya over a video consultation.
What the Research Shows About Pregnancy
The useful way to read these numbers is as a list of things to watch for, so that each one is caught early. The figures below compare women with a bicornuate uterus to women without one. They describe higher odds, not certainties, and many women with this uterine shape carry to term without any of these problems.
Preterm birth. This is the most consistent finding. In the review above, unification defects were associated with about three times the rate of preterm birth (RR 2.97) (Chan YY et al., Ultrasound Obstet Gynecol, 2011, PMID 21830244). A large bicornuate-specific study, which looked at more than 6,000 deliveries in a US national hospital database, found about 2.8 times the odds of preterm delivery and higher odds of the waters breaking early (PPROM) (Kadour Peero E et al., J Perinat Med, 2022, PMID 35946504).
A weaker cervix. The same cohort found that a bicornuate uterus was an independent risk factor for cervical insufficiency, where the cervix shortens or opens too early in the second trimester (Mastrolia SA et al., J Matern Fetal Neonatal Med, 2017, PMID 27903074). This is one of the main reasons cervical length is watched more closely.
Baby’s position. With less room in each horn, a baby is less likely to settle head-down. Unification defects were linked to nearly four times the rate of malpresentation (RR 3.87) (Chan YY et al., Ultrasound Obstet Gynecol, 2011, PMID 21830244). A tertiary-centre cohort of women with uterine anomalies of several types, bicornuate included, found breech presentation far more often than in women with a normally shaped uterus (Hua M et al., Am J Obstet Gynecol, 2011, PMID 21907963). Our post on why babies stay breech and the delivery options covers what happens next.
Placenta and growth. The same US database study found higher odds of placenta previa (aOR 1.7), placental abruption (aOR 3.0), preeclampsia (aOR 1.4) and a baby who is small for gestational age (aOR 2.9) (Kadour Peero E et al., J Perinat Med, 2022, PMID 35946504). This is why growth scans are usually scheduled more often than in a routine pregnancy.
Around delivery. The US database study also found somewhat higher odds of heavy bleeding after birth (aOR 1.4) (Kadour Peero E et al., J Perinat Med, 2022, PMID 35946504). Caesarean births are more common too. In the same tertiary-centre cohort of women with uterine anomalies, the odds of a first caesarean were raised even when the baby was not breech, so position is only part of the reason (Hua M et al., Am J Obstet Gynecol, 2011, PMID 21907963).
One caution on all of this: these are hospital and database studies, and women whose anomaly was found because of a problem are more likely to be counted than women who had smooth pregnancies and were never scanned for it. The risk for a woman with a partial bicornuate uterus and no history of loss may well be lower than these averages suggest.
Is Surgery Needed?
Usually not. The operation for a bicornuate uterus is an abdominal metroplasty (the Strassman procedure is the classic version), in which the two horns are opened and joined into one cavity. It is major surgery on the uterus, it leaves a scar in the uterine wall that has to be considered in every later pregnancy, and the evidence for it comes mainly from small case series rather than trials.
For these reasons, most gynaecologists keep it for a small group: women with repeated pregnancy losses where a thorough workup has found no other cause and the bicornuate shape is the most likely explanation. For almost everyone else, the plan is good monitoring during pregnancy, not surgery before it.
This is the clearest practical difference from a septate uterus, where a short hysteroscopic procedure through the cervix may be considered for selected women, mainly those with repeated losses, after discussing its uncertain benefit and risks. If an HSG or 2D scan has raised the question of surgery, confirm the exact diagnosis with 3D ultrasound or MRI first.
How Care Works During Pregnancy
A bicornuate uterus usually means your pregnancy is looked after as a closely monitored one. Our guide to what a high-risk pregnancy label means and how care works explains that this is about more frequent checks, not about expecting problems. In practice, that tends to mean:
- An early scan to locate the pregnancy. The pregnancy usually develops in one horn. An early scan confirms where it is and gives a baseline.
- Cervical length scans in the second trimester. Many obstetricians measure the cervix by transvaginal scan at intervals from mid-pregnancy, because of the link with cervical insufficiency. If it shortens, progesterone or a stitch may be offered. Our posts on short cervix and cervical length and the cervical stitch (cerclage) explain both.
- Growth scans in the third trimester. These check the baby’s growth and the blood flow through the placenta. Our guide to reading a growth scan and Doppler report walks through the numbers.
- Blood pressure and urine checks at every visit, for early signs of preeclampsia.
- A position check from about 36 weeks. If the baby is breech, your obstetrician will discuss whether turning the baby is suitable. With an unusual uterine shape, this is decided case by case.
- A delivery plan. Many women with a bicornuate uterus have a vaginal birth when the baby is head-down. A planned caesarean is more likely when the baby is breech or lying across. Our normal delivery vs C-section guide covers how that decision is made.
Practical Steps You Can Take
- Get the diagnosis confirmed. If the label came from an HSG or a 2D scan, ask whether a 3D ultrasound or MRI is needed to separate bicornuate from septate before any surgery is discussed.
- Carry your report. Show the scan report to every new doctor and scan centre in pregnancy, so the anomaly is known from the first visit.
- Book with a hospital that can manage early delivery. Choose a hospital with a blood bank and access to a neonatal unit, so that if your baby arrives early, the care is already in place.
- Learn the signs of early labour. Regular tightening, low back ache that comes and goes, pelvic pressure, a change in discharge or a leak of fluid are reasons to contact your hospital’s maternity unit straight away, without waiting to see if they settle. Our post on preterm labour signs and what to do lists them in full.
- Look after the basics. Folic acid before and during early pregnancy, a balanced home diet with dal, curd, greens and seasonal fruit, and gentle daily movement support every pregnancy, including this one.
At Fertilia, the Pregnancy Care program works alongside your obstetrician and hospital team, helping you understand each scan, prepare questions for your visits, and keep the rest of your health steady between appointments.
FAQ: Bicornuate Uterus and Pregnancy
Can I get pregnant naturally with a bicornuate uterus?
Yes, in most cases. A bicornuate uterus does not affect ovulation, the fallopian tubes or egg quality, and a systematic review found that this group of uterine anomalies does not reduce fertility. If conception is taking time, the standard fertility tests still apply, and the cause is usually something other than the uterine shape.
What is a heart-shaped uterus?
“Heart-shaped uterus” is the everyday name for a bicornuate uterus. The top of the uterus has an inward dip on the outside, so the organ looks like a heart on a 3D scan or MRI, with two horns joined lower down.
What is the difference between a bicornuate and a septate uterus?
A bicornuate uterus has an abnormal outer shape, with a dip at the top. A septate uterus has a normal outer shape, with a band of tissue dividing the cavity on the inside. A septum can often be removed through the cervix in a day procedure; a bicornuate uterus is rarely operated on. A 3D ultrasound or MRI tells the two apart.
Does a bicornuate uterus cause miscarriage?
It can be linked to a somewhat higher chance of pregnancy loss, but the larger and more consistent effect is on preterm birth and the baby’s position. Many women with a bicornuate uterus have no losses at all. If you have had two or more losses, a full recurrent-miscarriage workup is worth doing before attributing them to the uterine shape.
Does a bicornuate uterus need surgery before pregnancy?
Usually not. The operation (abdominal metroplasty) is major surgery and is generally kept for women with repeated losses where no other cause has been found. For most women, careful monitoring during pregnancy is the plan.
Will I need a caesarean with a bicornuate uterus?
Not automatically. A vaginal birth is often possible when the baby is head-down. Caesarean births are more common in women with a bicornuate uterus, partly because the baby is more likely to be breech or lying across. The decision is made near term, based on the baby’s position and how the pregnancy has gone.
Can a bicornuate uterus be seen on a routine scan?
Sometimes. A 2D scan or HSG may show a divided cavity, but it cannot reliably tell a bicornuate uterus from a septate one. A 3D transvaginal ultrasound, or an MRI when that is unclear, shows the outer shape of the uterus and confirms the diagnosis.
A bicornuate uterus is a difference in shape you were born with, and it usually comes to light only because a scan happened to look. With the right diagnosis, a cervical length check in mid-pregnancy, growth scans later on and a delivery plan made in good time, many women with this finding go on to hold their babies.
If you would like to go through your scan report or plan a pregnancy with this diagnosis, you can speak with Dr. Suganya over a video consultation, from anywhere in India.